Emergency pain is unpleasant. It gets here with sirens, in crowded waiting rooms, on football ovals, at roadside barriers. It can be a torn shoulder shouting at rest, a smashed hand that looks stealthily great, or a postoperative abdomen where pain leaps with every cough. The job in those minutes is not to philosophize regarding pain, yet to measure, reduce, and check it fast, safely, and with the person's trust fund. The national unit PUAEME008 Provide Pain Administration orders what skilled responders and medical professionals do when seconds issue and resources are irregular. Having actually educated crews in city ambulance services and remote commercial websites, and having rested next to adequate individuals to understand what helps and what harms, I see PUAEME008 as a toolkit for practical judgment as long as a collection of protocols.
What PUAEME008 asks of you in the real world
PUAEME008 Supply Pain Administration concentrates on structured assessment, secure selection of analgesic options within your range, alert surveillance, and prompt acceleration. It is educated across markets because pain is a global threat multiplier. An individual in extreme discomfort takes a breath shallowly, guards motion, spikes in blood pressure, and can lose composure. That waterfall complicates whatever from diagnostics to respiratory tract monitoring. The majority of pain administration courses cover ranges and medicine names. A great pain management certification program goes even more, demanding context: the individual's physiology, the atmosphere, offered equipment, and the way pain behaves over mins instead of hours.
The competency map behind PUAEME008 has 3 pillars. Initially, quick evaluation that incorporates pain intensity with system of injury, warnings, and feature. Second, treatment options calibrated to range and setup, from nonpharmacological measures up to inhaled analgesia or, where allowed, opioid titration. Third, continuous review, documents, and handover that can take on both medical examination and legal review.
Rapid assessment that values time and tissue
I teach pupils to believe in loops instead of lines. The very first loophole is security, ABCs, and perfusion. If the airway is noisy and the radial pulse is thready, pain monitoring waits. Once you have breathing and blood circulation in control, you can turn to pain with the same discipline.
Start with the patient's own words. Request a ranking using a 0 to 10 numeric range. If the person struggles with numbers, utilize a faces scale or easy language: no pain, moderate, moderate, severe, worst. Anchor what the number suggests. I commonly say, "Absolutely no is no discomfort, ten is the worst discomfort you can picture." A score of 7 with superficial breathing and face grimace is not the same as a calm 7 explaining tight upper body stress. Numbers are signals, not verdicts.
Then probe mechanism and quality. A clean cut laceration stings and throbs. A femur fracture has deep, movement-triggered pain that radiates. Colicky right top quadrant pain points to biliary problems; pleuritic chest discomfort boosts with ideas. Your inquiries must aim at pattern acknowledgment and danger. Is the discomfort brand-new, abrupt, tearing, pressure like, positional? Does it change with motion, palpation, or respiration? In an emergency setting, you measure discomfort not simply to relieve suffering, but to rule out the devastating: burst ectopic maternity, coronary infarction, acute abdomen, area syndrome, spinal cord compression.
Objective procedures issue. Record respiratory system price, oxygen saturation, heart price, high blood pressure, temperature, and level of awareness. Note pain habits: protecting, grimacing, diaphoresis, agitation. In nonverbal adults or children, empirical devices like FLACC assistance translate behavior into a rating. I lug a mental list. If pain drives tachycardia and high blood pressure in a previously normotensive individual, anticipate analgesia to help maintain vitals. If discomfort and hypotension ride with each other, beware with representatives that can drop high blood pressure further.
Immobilization and positioning matter as very early interventions. Splint a thought fracture before giving opiates if you can do it delicately. Boost and use ice bags to soft tissue injuries, protecting the skin. Urge sluggish, diaphragmatic breaths in rib injuries. A pillow under flexed knees relieves stomach guarding. These are not placebo steps. They reduce outer nociceptive input, which buys time and needs no prescription.
Matching treatment to range and risk
A normal PUAEME008 offer pain management framework highlights acting within your qualifications and procedures. In Australia, numerous initial responders and some workplace medics carry inhaled methoxyflurane, oral analgesics, and in some cases intranasal fentanyl. Nurse practitioner and paramedics might hold broader extents with titrated IV opioids or ketamine. In a country facility or mine website, you might have a lean kit and forty minutes to the local healthcare facility. The best pain monitoring training instructs you to stretch your options without overstepping.
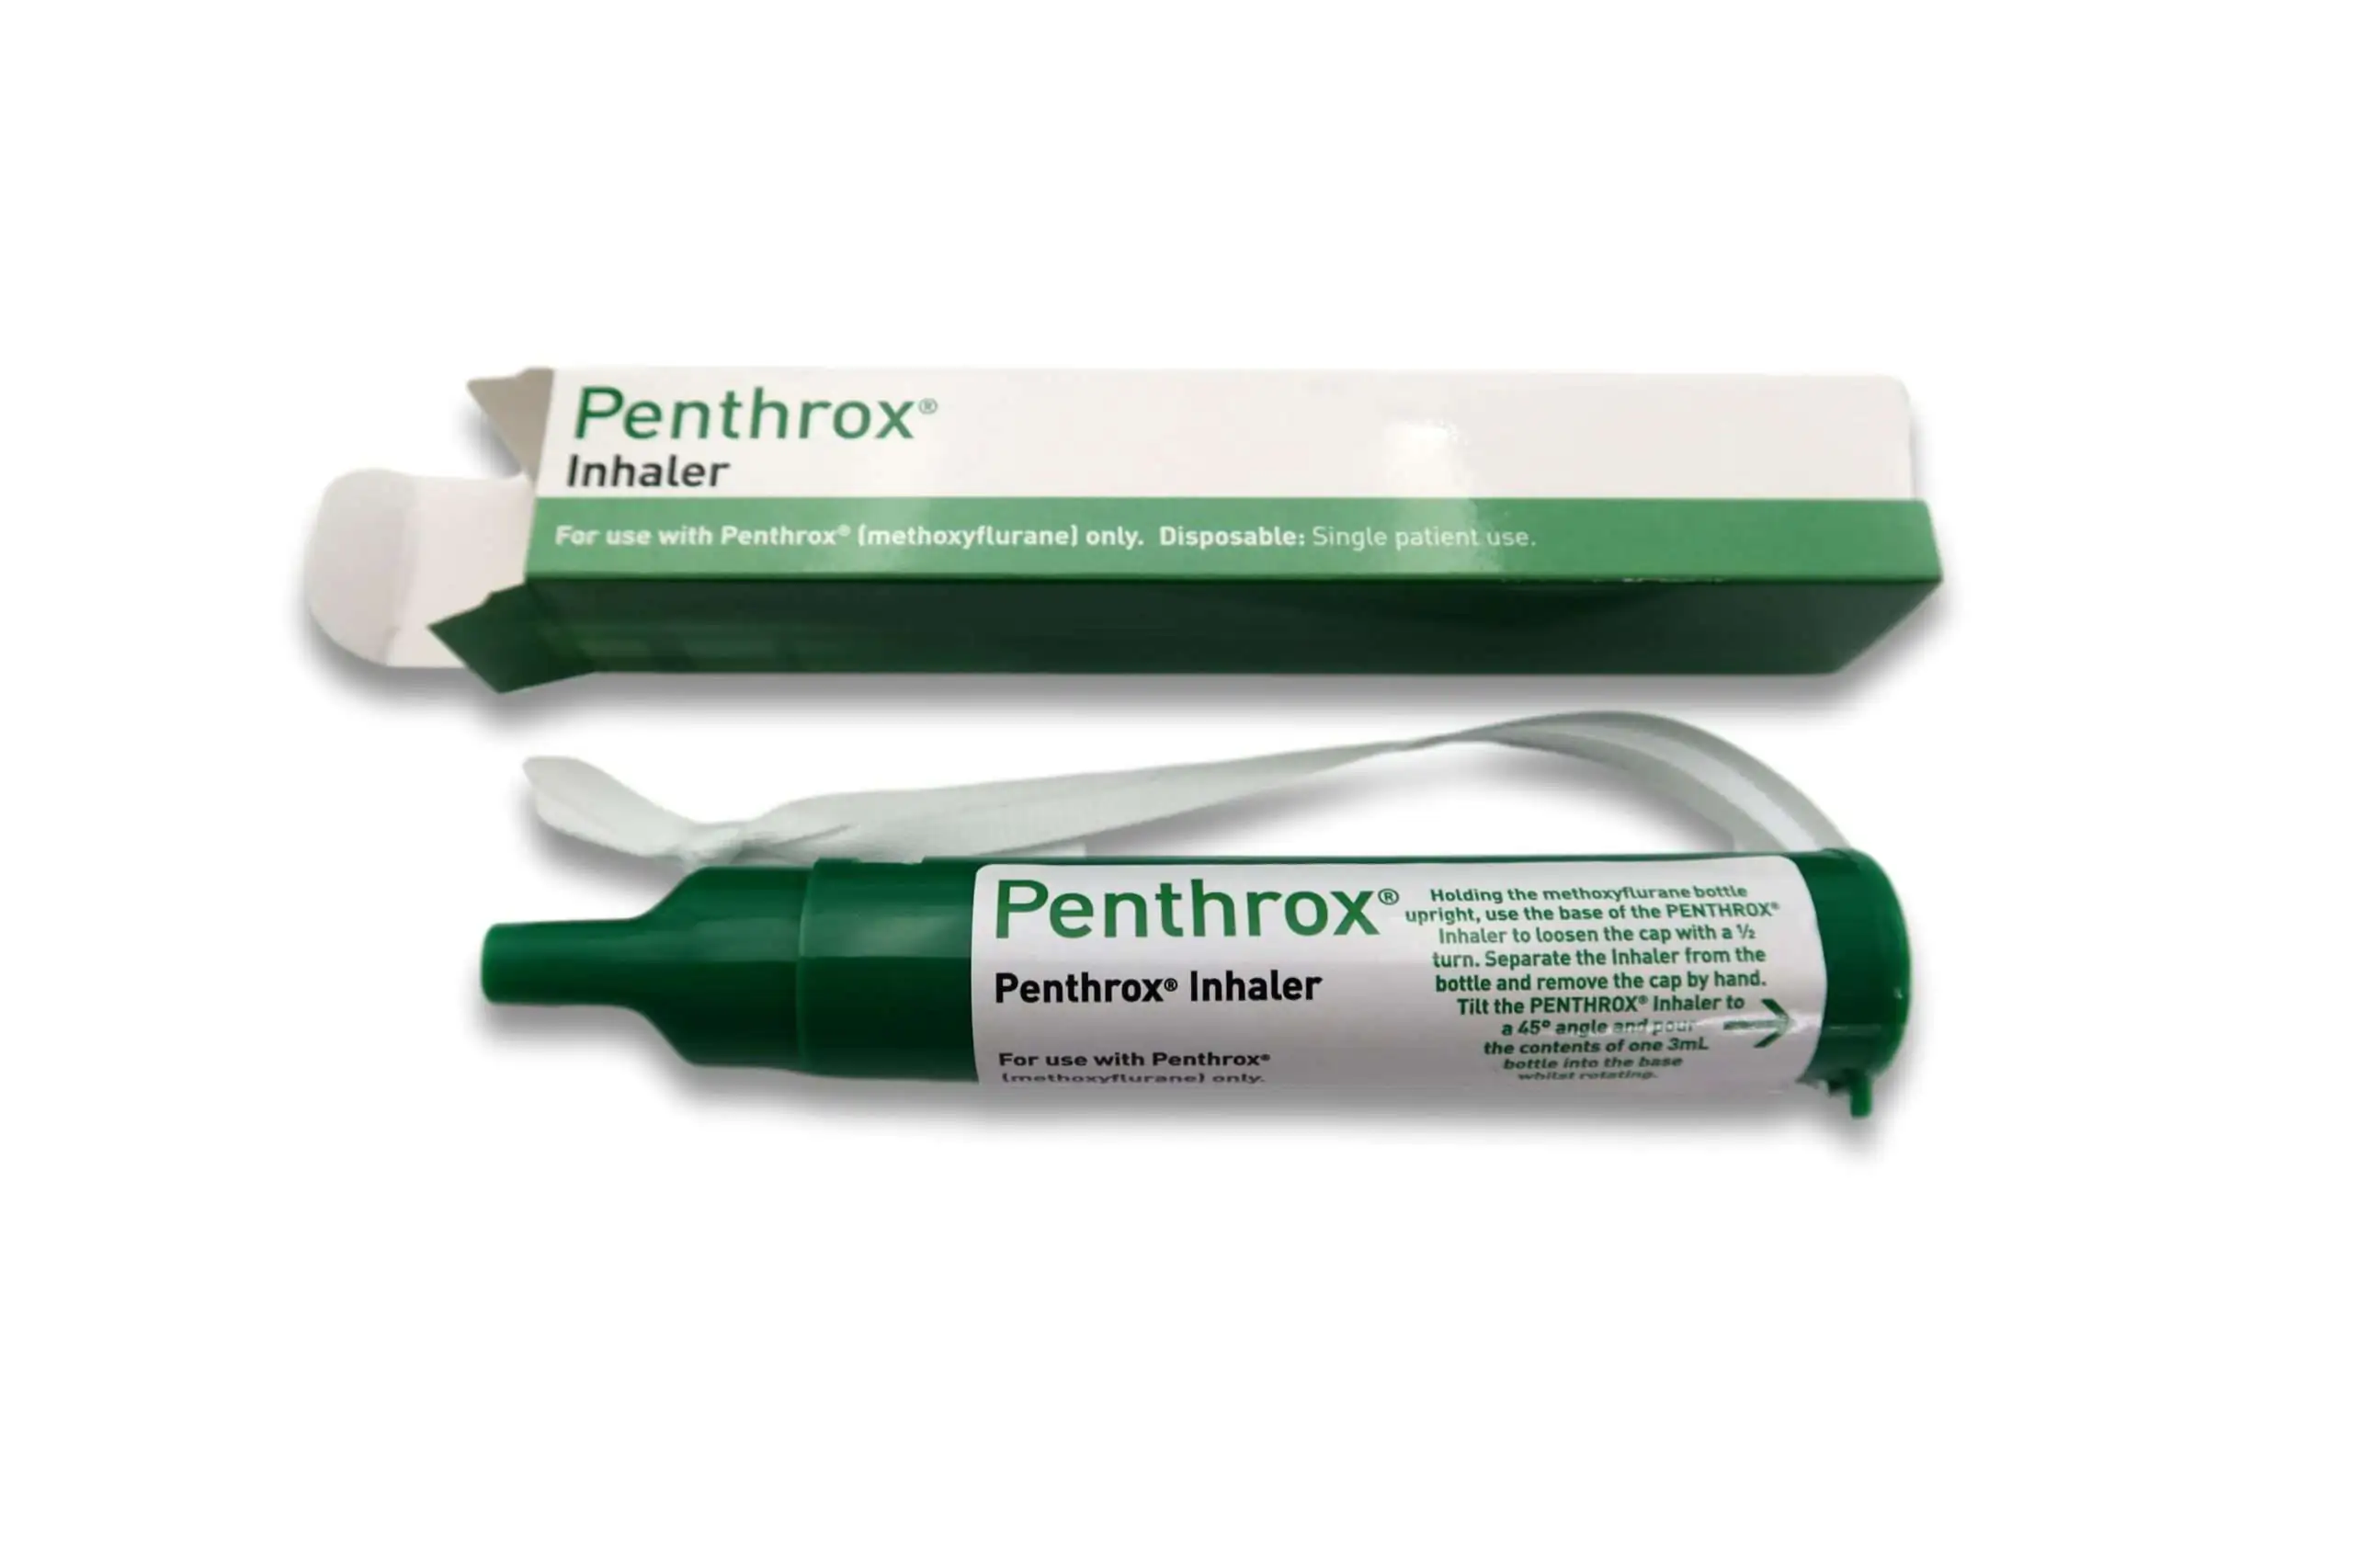
Methoxyflurane attracts dispute because it is straightforward, familiar, and not benign. It works swiftly for moderate to extreme injury pain, noticeable alleviation in two to three minutes with self-administered control. The pros are rate and simplicity. The cons include dizziness, sleepiness, and a ceiling impact. It is likewise best prevented in significant hypotension and in those with kidney danger. In method, if I have a mindful trauma individual with a lengthy transport and secure vitals, methoxyflurane can be a bridge. Maintain the individual supine or seated firmly, monitor for sedation, and log overall dose.
Intranasal fentanyl, where allowed, is a workhorse for severe discomfort. Absorption is rapid, dosing is straightforward, and venous accessibility is not required. It suits fractures, burns, and big soft tissue injury. The threat profile needs regard: breathing clinical depression is unusual in titrated dosages, but not impossible, specifically in opioid naive senior or those with existing together sedatives. Have oxygen prepared, monitor end tidal carbon dioxide if you bring capnography, and reassess every couple of minutes. My rule is to titrate to operate, not to absolutely no. If the client can tolerate motion and breathe typically at remainder, that suffices in a field setting.
Opioids offered IV belong to qualified extents and clear protocols. Morphine and fentanyl vary in kinetics and histamine launch, with morphine more likely to drop blood pressure in the volume depleted. For trauma where bleeding is feasible, I favor small aliquots of fentanyl, titrated, while loading fluid judiciously. For metabolic or renal pain, such as ureteric colic, IV opioids work, but take into consideration adjuncts like antiemetics and, where recommended, NSAIDs if renal function enables. Good discomfort administration training courses for registered nurses and paramedics emphasize the factors behind these options, not just memorizing lists.
Ketamine gains its location for severe injury pain, especially if hypotension is a risk. Dissociative dosing for analgesia at subanesthetic levels does not compromise respiratory tract reflexes and frequently boosts it by lowering frustration. The dissociation can be upsetting to people and carers; a positive explanation ahead of time helps: "This medicine alleviates discomfort and your brain may feel removed. I will certainly stick with you and chat you via it." Expect hypersalivation, nystagmus, and rare development responses. In the area, the benefits frequently outweigh the drawbacks, specifically if extrication is rough.
NSAIDs and paracetamol add more than they are often credited for, especially in bone and joint and dental pain. Dental or IV paracetamol is safe throughout a wide range, mindful of hepatic limitations. NSAIDs add anti inflammatory effect, effective in kidney colic and soft cells injuries, but prevent in believed blood loss, peptic abscess illness, renal problems, or late pregnancy. In other words transport setups, these may not act promptly; in lengthy transportations or in ED, they lower complete opioid requirement.
Nonpharmacological steps continue during transportation. Distraction, assisted breathing, and keeping the client cozy and covered are not details. They change understanding and reduce considerate drive. In pediatric medicines, bubbles, a moms and dad's voice, and quick, truthful explanations lower battle, which reduces pain.
The clock becomes part of the treatment
PUAEME008 stresses review, and for good reason. Discomfort is vibrant. The fracture that sits quietly on a stretcher roars when you round a corner. The abdominal discomfort that felt scattered at pickup centers to the right lower quadrant after twenty minutes. The pain in the back that is convenient with rest ends up being excruciating with leg weakness, indicating cauda equina. Every analgesic has a time to onset and a time to height. Deal with discomfort like a relocating target and you will stay clear of both over and under treatment.
Reassess discomfort ratings at details periods linked to the representative used: every five mins after intranasal fentanyl or IV opioids, every 10 to 15 minutes after oral or inhaled agents. Couple the score with crucial indicators, respiratory effort, and mental status. Documentation ought to read like a tale with time stamps. "13:10 - Patient states 8/10 sharp left forearm pain, deformity mid shaft distance, radial pulse existing. Methoxyflurane started. 13:14 - Pain 5/10, RR 18, SpO2 98, calmness, splint used. 13:20 - Discomfort 3/10, able to endure activity onto scoop."
Handover belongs to the treatment. A total record to the getting group protects against duplication, avoids overdosing, and appreciates the individual's experience. Include the preliminary evaluation, what you provided and when, what transformed, and any worries or warnings you noted. Knowledgeable pain monitoring training programs drill this practice to make sure that it continues under stress.
Safety webs and warnings that bypass routine
Most pain in emergency situation settings is straightforward. Some pain poses and penalizes complacency. PUAEME008 provide discomfort monitoring frameworks require acceleration when certain patterns appear.
A crushing main chest pain radiating to arm or jaw, particularly with diaphoresis and nausea, alters the top priorities. Analgesia needs to not postpone ECG and reperfusion pathways. If offering opioids, go slowly, enjoy high blood pressure, and prevent masking ongoing anemia signs. Nitroglycerin aids ischemic discomfort in chosen patients, yet it can drop pressure hazardously in appropriate ventricular infarct or in those that took phosphodiesterase inhibitors.
Acute serious headache referred to as abrupt and worst of life, particularly with neck tightness or neurological deficiency, points to subarachnoid hemorrhage or intracranial disaster. Aggressive opioid administration can jeopardize neurologic analysis. Aim for comfort, darkness, peaceful, and punctual transportation. Treat nausea. Stay clear of representatives that cloud consciousness unless respiratory tract and neuro tracking are assured.

Acute stomach discomfort in a pale, hypotensive patient requires marginal interference. Maintain them nil by mouth, placement of comfort, careful fluids, and fast transportation. NSAIDs would certainly be risky, as would certainly heavy opioids that mask peritoneal signs if surgical review looms. Where discomfort is extreme and activity inescapable, small titrated dosages to enable transfer are suitable, recorded clearly.
Severe pain in the back with brand-new saddle anesthetic, urinary retention, or bilateral leg weak point is a neurosurgical emergency. Discomfort relief issues, however the main work is speed. Record standard neuro status and protect the back during transfer.
Isolated limb trauma with pain out of proportion, strained areas, and worsening discomfort with passive stretch is an early compartment syndrome caution. Splinting and mild elevation assistance; ice in straight get in touch with fears me because of vasoconstriction. Escalate, reassess neurovascular condition continuously, and beware concerning over sedation that may hide deterioration.
Building individual rely on minutes
Pain is sensory and psychological. The fastest medications in the bag can not overcome mistrust. When I enter a confined room rescue or a home lounge, my first few sentences established the tone. I name myself, ask the patient's name, and claim clearly, "I'm going to help with your pain while we make a strategy." Consent, even when indicated, goes better with explicit choices. "You can breathe this medication while you hold the mouthpiece. It works quickly, and you're in control. I'll enjoy your breathing and ask just how it really feels." People who feel control demand much less medicine and recoup faster.
Cultural context issues. For some, admitting discomfort really feels weak. For others, vocalizing discomfort is the only method to obtain heard. A translator or a family member can help, but keep personal privacy and dignity where possible. In pediatric pain, I intend my explanations at the youngster and afterwards verify with the moms and dad. In senior people, check hearing and slow your words. Ask about home discomfort medicines and timing; polypharmacy adjustments take the chance of rapidly.
Training that sticks under pressure
There is no single discomfort monitoring training course that turns newbies right into masters. Skills develops with scenario repetition, comments, and direct exposure to variability. If you are selecting amongst pain administration courses, look for ones that require hands on practice, not just talks. A certification program hurting management need to include substitute surveillance, dosing calculations, contraindications, and documentation drills. For very first -responders and workplace paramedics, brief training courses in pain management that align with PUAEME008 supply sensible structures that are promptly usable. For medical professionals, pain management programs for nurses and discomfort monitoring courses for physiotherapists must extend past pharmacology right into interaction, useful analysis, and non medicine approaches that speed up rehabilitation.
An excellent pain monitoring certificate bolsters trustworthiness and aligns with business methods. In some territories, a pain monitoring accreditation training course may be required before bring methoxyflurane or providing intranasal opioids. For health center or prehospital personnel, discomfort management training for registered nurses focuses on titration abilities, sedation ranges, and escalation to medical testimonial. The objective is not a badge, yet a habit of secure, humane, reproducible care.
Documentation that does greater than satisfy policy
The list attitude can produce sterilized notes. Good records inform the medical story without dramatization or point of view. They capture baseline pain, function, vitals, the rationale for selected therapy, the dosages and times, the action, any kind of unfavorable effects, and the plan. If a client declines analgesia, document the deal, discussion of risks and benefits, and the person's words. If a language barrier exists, call the interpreter and approach. A record that shows clinical reasoning shields the client and the provider.
Auditing your very own situations educates more than any lecture. Review 3 or 4 charts a month and ask whether the discomfort score moved, whether reassessment was timely, and whether alternative representatives may have worked better. Teams that debrief after tough instances enhance faster than teams that do not. Keep it curious, not punitive.
Practical circumstances that evaluate judgment
Imagine a 32 years of age motocross motorcyclist with an obvious tib fib fracture, pain 9 out of 10, BP 122/76, HUMAN RESOURCES 108, SpO2 99 percent, GCS 15. You have methoxyflurane, intranasal fentanyl, and a vacuum splint. Beginning with placing, guarantee, and apply a fast handbook stabilization. Methoxyflurane gets very early relief while your partner preps the splint. After 2 mins, intranasal fentanyl at a traditional dose lowers the spikes throughout motion. You reassess pain to 4 out of 10 before packing. The client can breathe gradually, and transportation is smoother. You maintain talking, advise prior to bumps, and document times and responses.
Contrast that with an 83 year old on warfarin who slipped in the shower room, now with neck and back pain and brand-new left leg weak point. Pain 7 out of 10 at remainder, BP 158/90, HR 96, SpO2 96 percent. Below, immobilize delicately, avoid excessive opioids that shadow neurology, take into consideration small titrated doses if essential to permit transfer, and rise early for imaging. File baseline neuro standing, warfarin usage, and the time of last dose. The discomfort issues, yet the warnings matter more.
A 3rd circumstance: a 24 years of age with serious cramping reduced stomach pain, light and diaphoretic, HR 120, BP 92/60, last menstrual duration six weeks earlier. The chance of ectopic maternity increases. Keep her supine with legs a little pain management certification programs elevated, oxygen as required, IV gain access to, careful liquids, and transportation quickly. Analgesia must not postpone care; small titrated dosages to minimize distress are sensible, yet prioritizing speed and monitoring is the right phone call. Your documents will anchor later decisions.
Where physiotherapists and registered nurses suit the chain
Emergency discomfort administration is not just about code 1 actions. Pain reframed very early modifications trajectories in ED and on wards. Nurses triage discomfort on arrival, initiate standing orders for dental analgesia, and flag high danger presentations. Discomfort management training for registered nurses outfits them to identify poor control, to intensify for more powerful agents, and to check sedation ranges with roughness. Physio therapists come across acute pain during mobilization. Discomfort administration programs for physiotherapists that consist of education on timing analgesia prior to gait retraining, use of chilly or warmth properly, and breathing strategies can change a session from unproductive to critical. Their observations often spot of foot decline, radicular patterns, or unmodifiable discomfort that needs clinical review.

Multidisciplinary coordination makes analgesia https://jsbin.com/reqocirune much more effective. A registered nurse times dental or IV medications so a physiotherapist gets a 30 to 60 minute window of maximum impact. A physician adjusts dosing because the physio therapist keeps in mind that pain spikes after treatment but clears up within 20 mins. This cycle of monitoring and adjustment is a system level expression of PUAEME008 thinking.
When much less is much more, and when it is not
There is an easy to understand fear of over sedation. I share it, and I show it. Respiratory depression is rare with mindful titration, but uncommon is not never. The antidote to that threat is not under treating pain. It is prep work: surveillance, proper dosing, and readiness to interfere. The elderly patient with rib cracks that takes a breath shallowly as a result of pain goes to danger of pneumonia and respiratory system failing. Judicious opioid usage, nerve blocks where offered, and incentive spirometry protect against downstream harm. On the other hand, the patient with uncomplicated ankle joint strain that leaves with 20 opioid tablet computers as a result of a rushed script deals with a various injury. Pain management is a scientific skill improved discernment.
In the prehospital world, I see the lure to move fast and delay discomfort relief to the medical facility. That selection in some cases makes sense: a brief transportation in city settings with energetic hemorrhage control and air passage top priorities. More frequently, little, early, titrated analgesia changes the maneuver from cot transfer to abuse. It likewise improves vital signs and reduces frustration that can mask medical adjustments. Be wary of absolutes. Utilize your training, your methods, and your scientific eye.
Choosing training that alters behavior
The market for pain administration training is wide. Some discomfort monitoring certification programs use thick theory with slim technique. Try to find pain management programs that replicate the actual disorder: a loud scene, a missing out on item of kit, a second person calling out, a time crucial warning. A supply discomfort management program aligned to PUAEME008 must cover:
- Scenario based assessment that integrates discomfort scales with device, vitals, and red flags. Medication option and titration within range, consisting of methoxyflurane, intranasal representatives, and IV alternatives where permitted. Nonpharmacological strategies and splinting under pain load. Monitoring, adverse impact recognition, and risk-free handover.
Beyond certifications, go for refreshers. Abilities plain without usage. A discomfort monitoring accreditation renewed every a couple of years with interim drills maintains self-confidence high. If you are a manager, send out sets or teams, not solo learners. Interaction and role quality around analgesia typically fall short at the team degree, not the individual.
The ethics of relief
Pain is subjective, yet our responsibilities are not. We owe clients earnest efforts to lower suffering, within risk-free limits. We owe culture mindful stewardship of controlled substances. PUAEME008 sits in the center of those responsibilities, asking you to act emphatically and attentively. The person howling in the back of the vehicle, the kid with a busted forearm, the older with a hip crack, all deserve your ideal. That indicates a methodical approach, a dose of mankind, and the discipline to revisit your decisions as the situation evolves.
Emergency discomfort monitoring is not attractive. It is a craft of little moves done on schedule. Ask, look, touch gently, support, dosage, watch, file, hand over. Repeat. If you seek a discomfort management certification, choose one that evaluates your judgment as long as your memory. If you instruct, stress realism. If you lead, back your groups when they choose humane, monitored analgesia. Discomfort will never be simple. Our approach can be.